This rehabilitation protocol is designed for patients recovering from arthroscopic Bankart repair and capsulolabral stabilization procedures for anterior shoulder instability.
The shoulder is the most mobile joint in the body and depends heavily on soft tissue structures for stability. Following a dislocation or recurrent instability event, the labrum and capsule may detach from the glenoid, leading to persistent instability, pain, weakness, apprehension, and recurrent dislocations.
The goal of surgery is to restore stability by repairing the detached labrum and capsule back to the glenoid. The goal of rehabilitation is to safely protect the repair while gradually restoring mobility, strength, neuromuscular control, and confidence with overhead movement.
This protocol follows a conservative, criterion-based progression designed to prioritize biological healing while minimizing stiffness, muscular compensation, and recurrent instability risk.
Progression should always be individualized based on:
- Surgical findings
- Tissue quality
- Number of anchors utilized
- Presence of bone loss
- Associated procedures performed
Patient age and sport demands, pain and inflammatory response, movement quality, and neuromuscular control should guide progress. Close communication between the patient, physical therapist, athletic trainer, and surgical team is encouraged throughout the recovery process.
Understanding Shoulder Instability
What Is a Bankart Lesion?
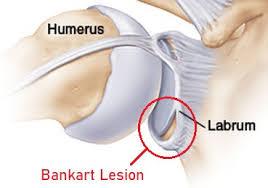
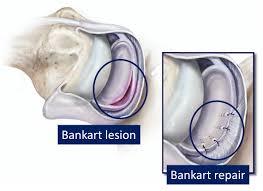
The labrum is a fibrocartilaginous rim that deepens the shoulder socket and contributes significantly to shoulder stability. During a shoulder dislocation, the anterior-inferior labrum and capsule may tear away from the glenoid rim. This injury is known as a Bankart lesion.
Once the stabilizing structures are detached, the shoulder may continue to feel unstable, painful, weak, or prone to recurrent dislocation.
Common Symptoms of Shoulder Instability
- Recurrent dislocations or subluxations
- Pain with overhead activity
- Apprehension when the arm is abducted and externally rotated
- Weakness during pushing or lifting
- Sensation of looseness or shifting
- Difficulty returning to sport
Goals of Arthroscopic Stabilization
Arthroscopic Bankart repair restores stability by:
- Reattaching the labrum to the glenoid rim
- Tightening the capsule
- Restoring shoulder stability mechanics
- Improving dynamic shoulder control
- Reducing recurrent instability risk
Healing of the repaired labrum and capsule occurs gradually over several months. Early protection is critical to avoid excessive stress on the repair.
General Rehabilitation Principles
Early Priorities
- Protect the repair
- Control pain and inflammation
- Restore safe passive mobility
- Prevent muscular inhibition
- Maintain scapular control
- Avoid recurrent instability stress
Long-Term Priorities
- Restore full shoulder mobility
- Rebuild rotator cuff strength
- Optimize scapular mechanics
- Improve dynamic shoulder stability
- Restore overhead athletic function
- Safely return to sport and training
Postoperative Expectations
Common Early Symptoms
- Shoulder tightness or stiffness
- Mild swelling and bruising
- Fatigue with arm positioning
- Sleep discomfort
- Temporary weakness
- Mild soreness with exercises
Contact Your Surgeon If You Experience:
- Fever greater than 101°F
- Significant redness or drainage
- Increasing swelling or severe pain
- Shortness of breath
- Progressive numbness or weakness
- Calf pain or swelling
Rehabilitation Timeline Overview
| Phase | Timeline | Primary Goals |
|---|---|---|
| Phase I | Weeks 0-2 | Protection, pain control, protected mobility |
| Phase II | Weeks 2-6 | Progressive ROM and muscular activation |
| Phase III | Weeks 6-12 | Strength restoration and neuromuscular control |
| Phase IV | Months 3-4 | Advanced strengthening and dynamic stability |
| Phase V | Months 4-6+ | Return-to-sport progression |
PHASE I — PROTECTION & EARLY MOBILITY (Weeks 0-2)
Goals
- Protect surgical repair
- Control pain and inflammation
- Prevent stiffness within protected ranges
- Maintain elbow, wrist, and hand mobility
- Initiate scapular activation
Sling Use
- Sling with abduction pillow worn at all times unless performing exercises or hygiene
- Sleep in sling during this phase
- Avoid unsupported arm positioning
Precautions
- No active shoulder motion
- No lifting, pushing, or pulling
- Avoid excessive external rotation
- Avoid extension behind the body
- Avoid sudden shoulder movements
- Avoid supporting body weight through the arm
Recommended Interventions
Mobility: Pendulum exercises, Passive forward elevation within protected range, Passive external rotation to surgeon-directed limits, Elbow, wrist, and hand ROM
Scapular Activation: Scapular retraction, Scapular setting drills, Gentle shoulder shrugs
Pain & Swelling Management: Cryotherapy, Positioning strategies, Sleep support education
Patient Education Focus: Tissue healing timelines, Importance of sling compliance, Safe movement strategies, Sleep positioning, Activity modification
Criteria to Progress
- Pain controlled
- Incisions healing appropriately
- Tolerates protected passive ROM
- No signs of instability
- Good compliance with precautions
PHASE II — PROTECTED MOTION & EARLY ACTIVATION (Weeks 2-6)
Goals
- Continue protecting repair
- Gradually restore passive mobility
- Initiate gentle muscular activation
- Improve scapular control
- Prevent stiffness while avoiding instability stress
Mobility Guidelines
- Gradual progression of passive ROM
- External rotation advanced cautiously
- Avoid aggressive stretching
- Avoid apprehension positions
Recommended Interventions
Mobility: Passive forward elevation progression, Supine external rotation progression, Assisted elevation drills, Gentle behind-the-back mobility as tolerated later in phase
Early Strengthening: Isometric internal and external rotation, Rotator cuff activation at neutral, Prone row progression, Sidelying external rotation, Scapular stabilization exercises
Neuromuscular Control: Rhythmic stabilization drills, Proprioceptive training, Scapular positioning drills
Cardiovascular Training: Walking program, Lower extremity conditioning, Stationary bike
Precautions
- Avoid forceful external rotation
- Avoid sudden traction forces
- Avoid overhead loading
- Avoid aggressive strengthening
Criteria to Progress
- Minimal pain and inflammation
- Improved passive ROM
- Good scapular mechanics
- Tolerates light strengthening without irritation
- No instability symptoms
PHASE III — STRENGTH RESTORATION & DYNAMIC CONTROL (Weeks 6-12)
Goals
- You may discontinue your sling use after week 6
- Restore active motion
- Improve rotator cuff strength
- Develop dynamic shoulder stability
- Improve neuromuscular control
- Restore functional movement patterns
Recommended Interventions
Mobility: Active ROM progression, Cross-body mobility, Controlled external rotation progression, Thoracic mobility drills
Strengthening: Theraband internal/external rotation, Scaption progression, Standing row progression, Serratus anterior strengthening, Closed-chain stabilization drills, Side-lying ER progression, Prone T, Y, and row progression
Neuromuscular Training: Rhythmic stabilization, Perturbation training, Wall stabilization drills, Reactive shoulder control
Movement Quality Focus
- Maintain scapular control
- Avoid anterior humeral head translation
- Avoid compensatory upper trapezius dominance
- Emphasize rotator cuff endurance
Cardiovascular & Conditioning
Elliptical, Running progression if appropriate, Lower body strength training
Criteria to Progress
- Full or near full ROM
- Good rotator cuff endurance
- Pain-free ADLs
- Improved dynamic shoulder control
- No apprehension symptoms
PHASE IV — ADVANCED STRENGTH & FUNCTIONAL PERFORMANCE (Months 3-4)
Goals
- Restore high-level shoulder strength
- Improve force absorption and dynamic stability
- Prepare for overhead athletic activity
- Improve muscular endurance and power
Recommended Interventions
Strength & Stability: Dumbbell strengthening progression, Landmine press progression, Push-up progression, Cable stabilization drills, Bottom-up carry progression, Turkish get-up progression, Advanced serratus strengthening
Dynamic Training: Medicine ball stabilization, Reactive perturbation drills, Closed-chain shoulder loading, Controlled overhead progression
Athletic Preparation: Interval throwing preparation, Overhead control drills, Deceleration training, Rotational core training
Precautions
- Avoid uncontrolled overhead loading
- Avoid painful instability sensations
- Progress load gradually
Criteria to Progress
- Symmetric ROM
- Good overhead control
- Adequate strength and endurance
- No instability symptoms
- Tolerates functional loading
PHASE V — RETURN TO SPORT & PERFORMANCE (Months 4-6+)
Goals
- Restore sport-specific performance
- Improve confidence with overhead activity
- Return to unrestricted athletic participation
- Reduce reinjury risk
Advanced Training
- Plyometric shoulder drills
- Overhead endurance progression
- Sport-specific strengthening
- Throwing progression
- Contact preparation drills
- Advanced closed-chain loading
Return-to-Sport Considerations
Return to sport should be individualized based on procedure performed, contact vs non-contact sport, strength recovery, dynamic stability, psychological readiness, movement quality, and functional testing.
Typical return timelines:
- Non-contact sport progression: approximately 4-5 months
- Contact or collision sports: approximately 6 months or greater
- Overhead throwing progression: individualized and gradual
Weight Training Considerations
Patients returning to strength training should progress gradually and emphasize movement quality over maximal loading. The following exercises should initially be modified or avoided due to increased anterior shoulder stress:
- Behind-the-neck shoulder press
- Behind-the-neck pulldowns
- Wide-grip bench press
- Deep dips
- Heavy incline press
- Heavy overhead triceps work
Physical Therapy Communication Notes
Please contact Dr. Ford regarding persistent stiffness, significant ROM loss, recurrent instability sensations, apprehension symptoms, persistent inflammation, delayed progression, or concerns for repair integrity.
Final Notes for Patients
Recovery after shoulder stabilization surgery requires patience, consistency, and gradual progression. While many patients begin feeling improved early in recovery, complete healing and restoration of shoulder stability takes several months. The rehabilitation process should prioritize movement quality, shoulder control, and gradual strengthening rather than rushing back to activity.