This rehabilitation protocol is designed for patients recovering from surgical repair of a small rotator cuff tear.
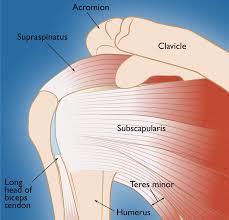
The rotator cuff is a group of four muscles and tendons that stabilize the shoulder and allow coordinated arm movement during lifting, reaching, throwing, pushing, and overhead activity.
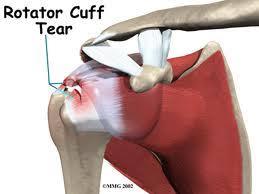
Rotator cuff tears may occur from acute injury, repetitive overhead activity, degeneration, or a combination of these factors.
The goals of rotator cuff repair surgery are to:
- Restore tendon attachment to bone
- Reduce pain and inflammation
- Improve shoulder strength and stability
- Restore functional movement
- Improve quality of life and activity tolerance
Healing of the repaired tendon into bone is a gradual biological process that continues for several months after surgery. Although many patients begin feeling better early in recovery, premature loading or aggressive progression may compromise tendon healing.
This protocol follows a conservative, criterion-based progression designed to protect the repair while gradually restoring mobility, strength, dynamic shoulder control, and long-term function.
Progression should always be individualized based on tear size and tissue quality, surgical fixation technique, pain and inflammatory response, strength progression, and occupational and recreational demands.
Understanding Rotator Cuff Tears
What Does the Rotator Cuff Do?
The rotator cuff consists of four muscles and tendons: Supraspinatus, Infraspinatus, Teres minor, and Subscapularis.
These structures help stabilize the shoulder joint, control arm movement, assist with lifting and reaching, and generate rotational strength.
Common Symptoms of Rotator Cuff Tears
- Pain with lifting or overhead activity
- Weakness
- Night pain
- Difficulty reaching
- Pain with throwing or sports
- Fatigue during repetitive activity
Why Early Protection Matters
Following repair, the tendon must biologically heal back into bone. During the early postoperative period, the repair site is vulnerable to excessive tension and overload. The rehabilitation process must balance protection of healing tissue, prevention of stiffness, gradual restoration of mobility, and progressive strengthening and movement control.
General Rehabilitation Principles
Early Priorities
- Protect tendon healing
- Control pain and inflammation
- Restore safe passive mobility
- Prevent stiffness
- Maintain scapular control
- Avoid excessive strain on the repair
Long-Term Priorities
- Restore shoulder mobility
- Rebuild rotator cuff strength and endurance
- Improve scapular mechanics
- Restore dynamic shoulder stability
- Safely return to work, lifting, and sport
Postoperative Expectations
Common Early Symptoms
- Shoulder soreness and tightness
- Sleep discomfort
- Swelling and bruising
- Temporary weakness
- Fatigue with arm positioning
- Mild discomfort during therapy
Contact Your Surgeon If You Experience
- Fever greater than 101°F
- Increasing redness or drainage
- Progressive swelling
- Severe uncontrolled pain
- Sudden loss of shoulder function
- Numbness or weakness
- Shortness of breath or calf pain
Rehabilitation Timeline Overview
| Phase | Timeline | Primary Goals |
|---|---|---|
| Phase I | Weeks 0-2 | Protection, pain control, passive mobility |
| Phase II | Weeks 2-6 | Protected mobility and early activation |
| Phase III | Weeks 7-14 | Strength restoration and neuromuscular control |
| Phase IV | Weeks 15-22 | Advanced strengthening and functional progression |
| Phase V | Months 6-9 | Return to activity and sport |
Important Early Precautions
- No lifting with operative arm
- No active shoulder elevation initially
- Avoid sudden shoulder movements
- Avoid excessive stretching
- Avoid supporting body weight through the arm
- Avoid forceful reaching behind the body
Protection of the tendon repair is critical during the first several weeks following surgery.
PHASE I — PROTECTION & PASSIVE MOBILITY (Weeks 0-2)
Goals
- Protect rotator cuff repair
- Control pain and inflammation
- Restore protected passive mobility
- Prevent stiffness
- Maintain elbow, wrist, and hand mobility
- Initiate scapular activation
Sling Use
- Sling (with or without abduction pillow) worn most of the time for 4-6 weeks
- Sleep in sling during this phase
- Remove sling only for exercises and hygiene
Precautions
- No active shoulder motion
- No lifting or carrying
- No sudden movements
- Avoid shoulder hyperextension
- Avoid excessive external rotation
Recommended Interventions
Mobility: Pendulum exercises, Supine passive forward elevation, Supine external rotation within protected limits, Elbow, wrist, and hand ROM
Scapular Activation: Scapular retraction drills, Gentle shoulder shrugs, Postural awareness training
Pain & Swelling Management: Cryotherapy, Sleep positioning strategies, Activity modification education
Movement Quality Focus
- Maintain relaxed shoulder posture
- Avoid compensatory shoulder hiking
- Emphasize controlled passive movement
Criteria to Progress
- Pain controlled
- Incisions healing appropriately
- Tolerates passive ROM program
- Minimal inflammatory response
- Good compliance with precautions
PHASE II — PROTECTED MOBILITY & EARLY ACTIVATION (Weeks 2-6)
Goals
- Continue protecting repair
- Gradually restore passive ROM
- Initiate controlled active-assisted movement
- Improve scapular stability
- Restore dynamic shoulder control
Precautions
- No aggressive stretching
- No heavy lifting
- Avoid painful movement patterns
- Avoid sudden loading
Recommended Interventions
Mobility: Progressive passive ROM, Active-assisted ROM progression, External/internal rotation progression in scapular plane, Flexion progression within tolerance
Early Strengthening: Submaximal pain-free isometrics, Rhythmic stabilization drills, Scapular isometrics, Light rotator cuff activation
Neuromuscular Training: Dynamic stabilization drills, Rhythmic stabilization at varying angles, Scapulothoracic control drills
Functional Activity: Light desk work as tolerated, Controlled daily activities below shoulder height, Driving once cleared and no longer using sling/pain medication
Movement Quality Focus
- Avoid upper trapezius dominance
- Restore proper scapulohumeral rhythm
- Emphasize smooth controlled motion
Criteria to Progress
- Full or near full passive ROM
- Minimal pain with exercises
- Appropriate scapular mechanics
- Tolerates early strengthening without flare-up
- Improved shoulder control
PHASE III — STRENGTH RESTORATION & NEUROMUSCULAR CONTROL (Weeks 7-14)
Goals
- You can discontinue wearing your sling after 6 weeks
- Restore active ROM
- Improve rotator cuff endurance and strength
- Restore dynamic shoulder stability
- Improve functional movement quality
- Gradually return to daily functional activity
Recommended Interventions
Strengthening: ER/IR tubing progression, Side-lying external rotation, Full-can progression, Prone row progression, Prone extension, Prone horizontal abduction, Biceps and triceps strengthening
Neuromuscular Training: Dynamic stabilization drills, Rhythmic stabilization, Closed-chain shoulder control, Reactive scapular stabilization
Functional Strength: Controlled reaching progression, Light lifting progression, Multi-planar movement training, Functional endurance drills
Movement Quality Focus
- Avoid shoulder hiking
- Maintain rotator cuff control during elevation
- Emphasize scapular positioning
- Restore smooth movement mechanics
Cardiovascular & Athletic Conditioning
Walking and bike progression, Lower body strength training, Core stabilization progression, Light functional activities as tolerated
Criteria to Progress
- Full active ROM with good mechanics
- Improved strength and endurance
- Minimal pain with strengthening
- Good scapular control
- No reactive inflammation
PHASE IV — ADVANCED STRENGTH & FUNCTIONAL PERFORMANCE (Weeks 15-22)
Goals
- Improve muscular strength and endurance
- Enhance dynamic shoulder control
- Restore higher-level functional activity
- Prepare for recreational and athletic progression
Recommended Interventions
Strength Progression: Progressive rotator cuff strengthening, Functional pressing and pulling patterns, Closed-chain stabilization drills, Multi-planar strengthening progression, Advanced scapular endurance training
Athletic & Recreational Preparation: Interval golf progression, Tennis progression if appropriate, Swimming progression, Sport-specific movement preparation
Functional Training: Carry progression, Light overhead activity progression, Occupational task simulation, Endurance circuit training
Weight Training Considerations
Patients returning to weight training should avoid heavy overhead pressing, sudden explosive lifting, aggressive behind-the-neck exercises, and heavy eccentric loading early in recovery. Load progression should prioritize movement quality and tendon tolerance.
Criteria to Progress
- Full pain-free ROM
- Good shoulder endurance
- Appropriate strength progression
- Functional activity tolerance
- Good movement quality during loading
PHASE V — RETURN TO ACTIVITY & SPORT (Months 6-9)
Goals
- Safely return to recreational and athletic activity
- Restore shoulder endurance and power
- Improve sport-specific movement quality
- Reduce reinjury risk
Advanced Training
- Progressive return-to-sport drills
- Advanced rotator cuff endurance training
- Plyometric progression if appropriate
- Throwing progression if indicated
- Functional strength maintenance
Physical Therapy Communication Notes
Please contact the surgical team regarding persistent stiffness, significant pain escalation, failure to progress ROM, excessive inflammation, concerns regarding repair integrity, persistent weakness, or delayed functional recovery.
Final Notes for Patients
Recovery after rotator cuff repair is a gradual process focused on protecting tendon healing while restoring shoulder function, strength, and endurance. Although many patients begin feeling improved early after surgery, complete tendon healing and recovery of shoulder performance takes several months.